

Robert A. Kyle
Multiple Myeloma Research and Treatments
Mayo Clinic
About
Research focus
Multiple Myeloma Research and Treatments
Impact
1,893 pubs · 115,198 cites · h-index 163
Affiliations
Publications
cohort · n=1325 mentionsJACC Highlight
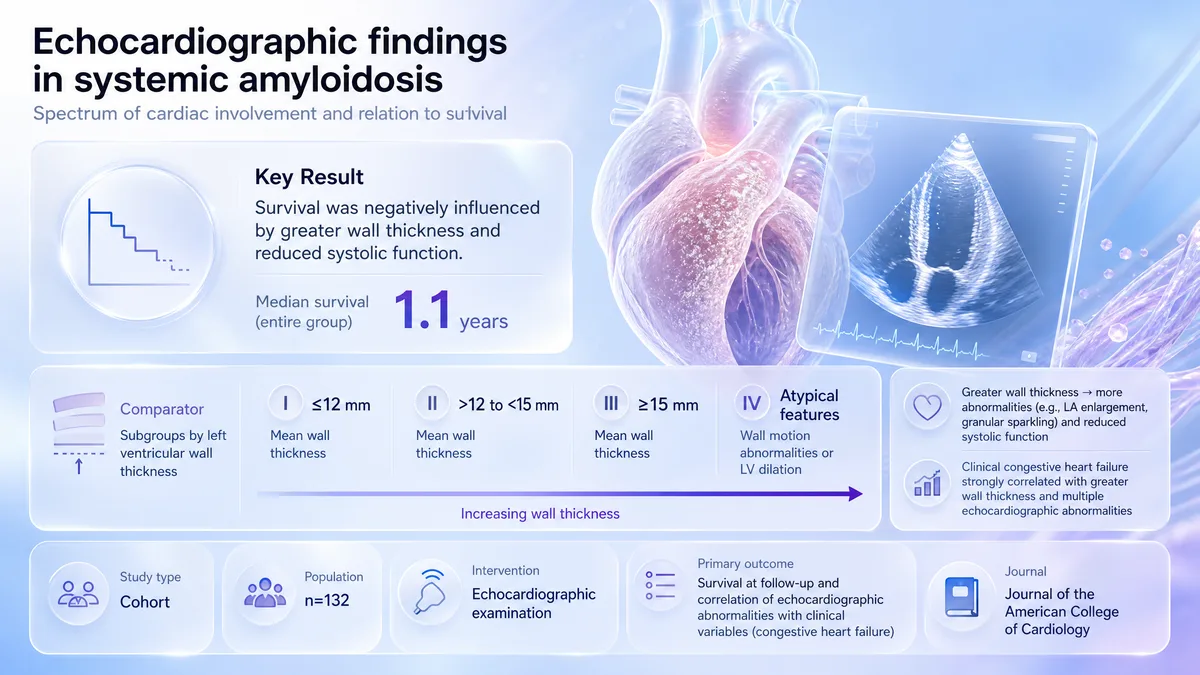
OCT 1985Cueto-GarciaJournal of the American College of Cardiology
Greater LV thickness and reduced systolic function predict a poor ~1.1-year median survival in systemic amyloidosis.
Echocardiographic wall thickness may aid prognosis in amyloidosis; leaves open validation with modern biomarkers and therapies.
cohort · n=36012 mentionsJACC Highlight
AUG 2016GroganJournal of the American College of Cardiology
Stage III patients (both biomarkers above cutoff) had an increased risk of mortality compared with stage I patients (HR 3.6; p < 0.001), with 4-year overall survival estimates of 18% vs 57% respectively.
May refine risk assessment in transthyretin cardiac amyloidosis; leaves open stage-specific therapy benefits pending validation.[[1]](https://pubmed.ncbi.nlm.nih.gov/27585505/)[[2]](https://www.jacc.org/doi/abs/10.1016/j.jacc.2016.06.
Retrospective Study
NOV 2025LinBlood
Clinical course, predictors of development, and therapeutic response in multiple myeloma with central nervous system involvement
Retrospective analysis reveals CNS involvement reduces survival in multiple myeloma, suggesting immune therapies may improve outcomes.
Original Research
NOV 2025DasariBlood
Genetic evolution of Waldenström macroglobulinemia across disease stages
Whole exome sequencing reveals mutational landscape in Waldenström Macroglobulinemia, indicating disease progression patterns.
Original Research
NOV 2025MannAfrican Journal of Marine Science
Catch trends and population status of the leopard whipray Himantura leoparda (family Dasyatidae) off the east coast of South Africa
The leopard whipray Himantura leoparda (family Dasyatidae) is globally assessed as Endangered on the IUCN Red List of Threatened Species owing to the species’ inherent vulnerability and declining population trends. In this study we assessed the population found off the coast of South Africa by modelling probability-of-capture using a comprehensive recreational shore-angling competition dataset covering a 46-year period (1977–2022, except not 2020). Although partially biased by ‘effort creep’, the results of JARA (Just Another Red-List Assessment) suggested that the population in South African waters is stable, and thus it was assessed as Least Concern. Decreased fishing effort, introduction of catch-and-release by competition anglers, and the establishment of large no-take marine protected areas within the core range of the species are the likely reasons for this conservation success. However, heavy fishing pressure on the population in southern Mozambique is cause for concern, and ongoing monitoring and careful management are required to ensure sustainable use of this resource.
Original Research
AUG 2025AskariBlood Cancer Journal
Value of serum-free light chain measurements in response and progression assessment in multiple myeloma with monoclonal protein measurable by electrophoresis
Retrospective analysis highlights serum-free light chain's role in assessing response and progression in multiple myeloma, suggesting its integration into clinical practice.
Prognostic Study
MAR 2025PaludoAmerican Journal of Hematology
Depth of Response From Fixed‐Duration Treatment Is Associated With Superior Survival in Waldenstrom Macroglobulinemia
As the treatment paradigm for Waldenström macroglobulinemia (WM) continues to evolve, the debate surrounding the prioritization of depth of response versus disease control as therapeutic goals gains significant relevance. However, the impact of depth of response from fixed-duration therapy on overall survival (OS) was unclear. This multicenter study evaluated the prognostic impact of depth of response using a landmark survival analysis. A total of 440 patients with WM treated with frontline fixed-duration regimens were included. Attaining a major response (MaR) was associated with superior outcomes, including significantly longer OS. The estimated 5-year PFS rates for patients with MaR at 6 months versus not were 50% versus 32%, respectively, p < 0.001, and the estimated 5-year OS rates for patients with MaR at 6 months versus not were 89% versus 70%, respectively, p < 0.001. In a multivariable analysis, MaR at 6 months was independently associated with superior PFS (HR 0.66, p = 0.007) and OS (HR 0.28, p < 0.001). Similar results were seen when considering deeper responses (CR + VGPR vs. PR). Depth of response at 6 months is an important prognostic marker in WM and an independent predictor of PFS and OS. These results support its utilization as a suitable endpoint in clinical studies in WM.
Prognostic Study
FEB 2025ZanwarBlood Cancer Journal
Clonal plasma cell proportion in the synthetic phase identifies a unique high-risk cohort in multiple myeloma
Risk stratification models based on cytogenetics and disease burden help identify high-risk patients with newly diagnosed multiple myeloma (NDMM). However, some high-risk patients remain undetected. This study evaluated the prognostic utility of the proportion of clonal plasma cells in the S-phase of the cell cycle for NDMM. Patients with active multiple myeloma diagnosed between 01/01/2013 and 01/31/2023 who underwent S-phase assessment were included. The S-phase proportion was calculated by analyzing DNA content between G0/G1 and G2/M peaks. Among 823 patients, 16% (135) had S-phase ≥2% at diagnosis. Patients with S-phase ≥2% exhibited significantly worse median progression-free survival (PFS) of 1.4 years (95% CI: 1.2-1.9) compared to 2.9 years (95% CI: 2.6-3.3) for those with S-phase <2% (HR 1.6, p < 0.0001). Median overall survival (OS) was also significantly lower at 3.9 years (95% CI: 2.9-5.7) versus 9.2 years (95% CI: 7.9-not reached; HR 2.2, p < 0.0001). Multivariate analysis confirmed S-phase ≥2% as an independent predictor of inferior PFS (HR 1.56, p = 0.001) and OS (HR 2, p < 0.0001) after adjusting for R2-ISS risk, age, renal function, and treatment strategies. Among patients with S-phase ≥2%, 53% (68/129) experienced progression-free survival (PFS) under 18 months with upfront therapy. Elevated S-phase was associated with a 2.5-fold higher risk of progression within 18 months [OR 2.55 (95% CI: 1.7-3.7), p < 0.001]. Patients with elevated S-phase but no IMS-high risk had a median OS of 5.7 years (95% CI: 4.7-9.2), similar to the IMS-high risk cohort without elevated S-phase (5.4 years, 95% CI: 4-NR). Those with both elevated S-phase and IMS-high risk had significantly worse OS (3.1 years, 95% CI: 1.6-NR, p = 0.043). These findings suggest that S-phase ≥2% is a powerful, independent prognostic marker for NDMM.
Prognostic Study
JAN 2025CharalampousBlood Advances
Solitary plasmacytoma: single-institution experience, and systematic review and meta-analysis of clinical outcomes
In this study, we first analyzed data from 147 patients with solitary plasmacytomas treated at the Mayo Clinic between 2005 and 2022 and then expanded our investigation through a systematic review and meta-analysis of 62 studies, encompassing 3487 patients from the years 1960 to 2022. Our findings reveal that patients with up to 10% clonal plasma cells in their bone marrow (BM), denoted as plasmacytoma +, had a significantly reduced median disease-free survival (DFS) of 15.7 months vs 79 months, P < .05, observed in patients with true solitary plasmacytomas, with no clonal cells in the BM. Risk factors identified for shorter DFS included the presence of clonal plasma cells in the marrow and a difference between involved and uninvolved free light chains of >5 mg/dL. The meta-analysis portion of our study highlighted a male predominance among patients, with a median age of 58 years, and confirmed radiation therapy as the predominant treatment modality. We also found that DFS rates at 3, 5, and 10 years were 66.9%, 55%, and 42.1%, respectively, and noted a significant difference in outcomes between patients with bone and extramedullary plasmacytomas, with the latter group exhibiting better survival rates. This dual-faceted approach provides a thorough overview of survival rates and critical risk factors for patients with plasmacytoma, underscoring the vital role of accurate disease staging at diagnosis and the impact of tumor location on patient prognosis.
Cohort Study
DEC 2024LeeLeukemia
Capillary leak phenotype as a major cause of death in patients with POEMS syndrome
Cause of death (COD) in POEMS (polyneuropathy, organomegaly, endocrinopathies, monoclonal protein and skin changes) syndrome is not well described. We investigated COD in patients with POEMS syndrome treated at Mayo Clinic between 2000 and 2022. Of the 89 deaths, 49 patients had known COD and were the subject of this study. Seventeen patients died of unrelated causes, while 32 patients (65%) died from causes related to POEMS syndrome including secondary malignancies like myelodysplastic syndrome and acute leukemia (n = 5) and complications from active therapy (n = 5). Notably, 19 patients died with a stereotypic syndrome we termed capillary leak phenotype (CLP), which was characterized by refractory ascites, effusions and/or anasarca that ultimately resulted in hypotension, renal failure and cardiopulmonary arrest. Alternate causes for these symptoms, such as cardiac and hepatic etiologies, were excluded. CLP as a COD was an earlier event with a median time from diagnosis to death of 2.5 years compared to 12.0 years for all other deceased patients (p = <0.0001). By definition, treatment of terminal CLP was unsuccessful with median survival of only 4 months after CLP onset. The driver of CLP is unknown, but recognition as an entity should allow for systematic study.
Retrospective Study
NOV 2024GoelBlood Advances
Retreatment of multiple myeloma with previously refractory drugs
Retrospective study reveals meaningful efficacy of previously refractory drug retreatment in multiple myeloma, indicating a viable option when novel therapies are unavailable.
Cohort Study
OCT 2024VisramBlood
Comparison of progression risk of monoclonal gammopathy of undetermined significance by method of detection
Monoclonal gammopathy of undetermined significance (MGUS) is an asymptomatic premalignant disorder. The current standard of care is not to screen for MGUS, so it is often incidentally diagnosed in the clinic. It is unknown whether the outcomes of screened vs clinically detected MGUS differ. We compared the progression risk between screened vs clinical MGUS cohorts and assessed whether the MGUS detection method affected risk prediction of established clinical factors (score). We included 379 screened MGUS cases from the Olmsted County population-based study and 1384 patients with MGUS diagnosed during routine clinical evaluation at Mayo Clinic. Median follow-up time for the screened vs clinical cohort was 26.6 and 40.1 years, respectively. Accounting for death as a competing risk, the cumulative incidence of progression at 25 years was similar in the screened (11.1% [95% confidence interval [CI], 8.3-14.8]) vs clinical (10.1% [95% CI, 8.6-11.8]) MGUS cohorts, even when stratified by sex, age, or the baseline MGUS risk score. Overall, 0.9 (95% CI, 0.6-1.2) of patients with screened MGUS vs 1.0 (95% CI, 0.9-1.2) of those with clinically detected MGUS experienced disease progression for every 100 person-years of follow-up. MGUS detection method did not modify the association between MGUS risk score and progression risk (pinteraction = 0.217) and did not add to known risk factors for progression (likelihood ratio test; P = .839). Here, we show that progression risk among patients with screened vs clinically detected heavy-chain MGUS was similar. Future studies are needed to assess whether tailored follow-up of patients with screened MGUS affects clinical outcomes.
Cohort Study
JUL 2024ChohanBlood
Multiomics analysis of IgM monoclonal gammopathies reveals epigenetic influence on oncogenesis via DNA methylation
Currently, the role of DNA methylation in the immunoglobulin M (IgM) monoclonal gammopathy disease spectrum remains poorly understood. In the present study, a multiomics prospective analysis was conducted integrating DNA methylation, RNA sequencing (RNA-seq), and whole-exome sequencing data in 34 subjects (23 with Waldenström macroglobulinemia [WM], 6 with IgM monoclonal gammopathy of undetermined significance [MGUS], and 5 normal controls). Analysis was focused on defining differences between IgM gammopathies (WM/IgM-MGUS) compared with controls, and specifically between WM and IgM-MGUS. Between groups, genome-wide DNA methylation analysis demonstrated a significant number of differentially methylated regions that were annotated according to genomic region. Next, integration of RNA-seq data was performed to identify potentially epigenetically deregulated pathways. We found that pathways involved in cell cycle, metabolism, cytokine/immune signaling, cytoskeleton, tumor microenvironment, and intracellular signaling were differentially activated and potentially epigenetically regulated. Importantly, there was a positive enrichment of the CXCR4 signaling pathway along with several interleukin (interleukin 6 [IL-6], IL-8, and IL-15) signaling pathways in WM compared with IgM-MGUS. Further assessment of known tumor suppressor genes and oncogenes uncovered differential promoter methylation of several targets with concordant change in gene expression, including CCND1 and CD79B. Overall, this report defines how aberrant DNA methylation in IgM gammopathies may play a critical role in the epigenetic control of oncogenesis and key cellular functions.
Original Research
MAY 2024ZanwarJournal of Clinical Oncology
Simplified Risk Stratification Model for Patients With Waldenström Macroglobulinemia
Patients with Waldenström macroglobulinemia (WM) have disparate outcomes. Newer therapies have emerged since the development of International Prognostic Scoring System, and
Original Research
MAY 2024KumarAmerican Journal of Hematology

Three‐dimensional telomere profiling predicts risk of progression in smoldering multiple myeloma
Smoldering multiple myeloma (SMM) is a precursor stage that precedes multiple myeloma (MM). SMM is heterogenous with nearly 40% of patients progressing to MM in the first 5 years. The high rate of progression of SMM patients highlights the need for early intervention, which underscores the importance of identifying SMM patients with the highest risk of progression. Several risk stratification models showed utility in identifying high‐risk SMM patients; however, these systems showed limited sensitivity. To date, identifying high‐risk SMM patients remains an important clinical need. In this study, we present the 3‐dimensional telomere profiling as a structural biomarker capable of stratifying SMM patients as a function of genomic instability. Quantifying telomere dysfunction using the TeloView technology showed utility in risk stratification of cancer patients, particularly hematological malignancies. In this study, we analyzed 168 SMM patients. We report an AUC in ROC analysis of 0.8 using a subset of the patients as a training dataset. We then conducted a blind validation on a different cohort and demonstrated a positive predictive value of 85% and negative predictive value of 73%, with sensitivity and specificity of 83% and 76%, respectively. We examined the correlation between the TeloView prediction and the 20‐2‐20 scoring system, and cytogenetic abnormalities. We report a correlation of 53% with the 20‐2‐20 scores and over 60% correlation with cytogenetic abnormalities. The result of this study presents the telomere profiling as an effective biomarker able to stratify SMM patients to their respective risk groups with high sensitivity and specificity.
Original Research
MAY 2024SteensmaMayo Clinic Proceedings
Sir Wilfred Thomason Grenfell: Medical Pioneer in Newfoundland and Labrador
Stamp Vignettes focus on biographical details and accomplishments related to science and medicine, and not individual views and prejudices except where they had a major impact on the subject's life. The authors do not intend to imply any endorsement of such views when discussing a Stamp Vignette on Medical Science. Stamp Vignettes focus on biographical details and accomplishments related to science and medicine, and not individual views and prejudices except where they had a major impact on the subject's life. The authors do not intend to imply any endorsement of such views when discussing a Stamp Vignette on Medical Science. Wilfred Thomason Grenfell was born in the village of Parkgate in Cheshire, England, on February 28, 1865, the second of 4 brothers. His father, Reverend Algernon Sidney Grenfell (1836-1887), served for many years as headmaster of Mostyn House School in Parkgate, a private boy's school that Wilfred attended for a few years before going on to Marlborough School in Wiltshire in 1879 at age 14. Mostyn House School was run by the Grenfell family from 1862 until its closure in 2010. Wilfred's older brother Algernon succeeded his father as headmaster and instituted several educational reforms during his 40-year tenure. Wilfred's mother, Jane Hutchinson (1832-1921), was the daughter of a British military engineer, and was born in Cossipore (now Kashipur), part of Kolkata, India. Wilfred counted 48 cousins in the British armed forces, and he planned an army or church career before a discussion with a village doctor in 1883, which prompted him to pursue medicine instead.View Large Image Figure ViewerDownload Hi-res image Download (PPT) In February 1883, Wilfred moved to London to study at the London Hospital Medical College, where he was an indifferent student. However, he was a keen athlete, spending much of his time on cricket, rugby, boxing, rowing, and operating a gymnasium and Sunday School out of his home. He also played rugby for Richmond Football Club (a real club, but not the inspiration for the fictional AFC Richmond in the Ted Lasso television series). He obtained a license in early 1888 from the Royal College of Physicians and membership in the Royal College of Surgeons, but he failed the Bachelor of Medicine exam set by University College of London. While a medical student in London, Grenfell was strongly influenced by surgeon Sir Frederick Treves (1853-1923). Dr Treves was noted for saving the life of King Edward VII when the king developed typhlitis just before his coronation in 1902, as well as for his friendship with "Elephant Man" Joseph Merrick (1862-1890), who spent the last 4 years of his life in London Hospital cared for by Dr Treves. Grenfell was also inspired by a tent religious revival sermon of traveling American evangelist Dwight Moody (1837-1899) and dedicated his life to practical Christian service. Grenfell and his mentor Dr Treves both enjoyed sailing and the sea. Treves suggested that Grenfell should join a new charitable organization called the National Mission to Deep Sea Fishermen (later renamed the Fishermen's Mission), which had been founded by Ebenezer Joseph Mather (1849-1927) in 1881. Grenfell was appointed as the mission's superintendent at the surprisingly young age of 24 in 1889. He first served as a surgeon on a hospital ship serving North Sea fisheries, which allowed him both to be of service to others and to indulge his inclination for adventure and physical activity. In 1892, the mission sent Grenfell to investigate conditions in coastal fishing villages in Labrador. Grenfell traveled up and down the coast in a hospital ship and became deeply concerned by both the lack of access to medical care and the poor living conditions in coastal fishing villages. He saw settlements that had been entirely destroyed by epidemics of diphtheria. He began to recruit physicians and nurses and set up a network of cottage hospitals and nursing stations along the Labrador coast; the first 2 were founded at Battle Harbour in 1893 and Indian Harbour in 1894. In 1901, the Mission opened a year-round hospital at St. Anthony on Newfoundland's remote Northern Peninsula, near the 10th century Norse/Viking landing site of L'anse aux Meadows. The St. Anthony community became the regional headquarters for Grenfell's efforts. On Easter weekend 1908, while travelling by dogsled to operate on a sick boy in rural Newfoundland, Grenfell drifted out to sea on a slab of ice and soon realized his life was in peril. Unfortunately, he had to kill the dogs to survive. After he was rescued by a passing ship, he set up a memorial to the dogs. He frequently retold this dramatic tale in lectures and published the story as a book, Adrift on an Ice-Pan. In 1912, the Fishermen's Mission no longer felt it could support Grenfell's efforts, since the scope of Grenfell's ambition in Newfoundland and Labrador exceeded what the mission's board was comfortable with. Grenfell had been funding his work largely on his own with proceeds from speaking tours (he was a popular and skilled lecturer) and royalties from a succession of books he published about life in Labrador and a number of religious topics. In 1914, Grenfell founded the International Grenfell Association (IGA) to continue his work. The IGA still exists and supports not-for-profit organizations that improve the health and social welfare in the region, although all facilities were turned over to the Newfoundland and Labrador government by 1981. Until 1979, hundreds of First Nations, Inuit, and other Indigenous children in Labrador were separated from their families and taken to residential schools run by the IGA or by Moravian missionaries. In addition to the loss of family and cultural connections, many of these children later reported that they were abused physically or sexually during their time at the schools. In 2017, Canadian Premier Minister Justin Trudeau apologized on behalf of the nation for how the children were treated at the schools, and approximately 1000 victims received a $50 million settlement from the Canadian government. In 1909, Grenfell married Anne Elizabeth Caldwell MacClanahan (1884-1938) who was from suburban Chicago. They met aboard the RMS Mauretania when he was returning from a fundraising trip to England. She was en route home from a 3-year world tour after graduating from Bryn Mawr College in Pennsylvania. Anne managed many of the administrative affairs for the Grenfell mission in St. Anthony and was an active participant in health and welfare work. The couple had 3 children. Grenfell was knighted by King George V in 1927 and received numerous honorary degrees, including one from the University of Oxford (1907) where he had spent one term playing rugby in the late 1880s. In 1931, Grenfell narrated part of an adventure film called The Viking. He described how the sealing ship SS Viking exploded during the making of the film, killing 25 crew including the movie's producer. Until a tragic fire in a studio in India during the 1989 filming of The Sword of Tipu Sultan, this represented the largest number of lives lost during production of a single motion picture. Grenfell retired to the small village of Charlotte, Vermont, in 1932, and spent winters on St. Simons Island, Georgia. At the time of his retirement, the IGA operated 6 hospitals, 4 hospital ships, 7 nursing stations, 2 schools, and 2 orphanages, as well as 14 cooperative industrial centers and a lumber mill providing employment for the local population. With his health declining, Grenfell resigned from the IGA in 1936, and he died in Vermont on October 9, 1940, from a myocardial infarction following a croquet match. His ashes were brought to St. Anthony in Newfoundland, to be scattered on a rock face on which he had scattered his wife Anne's ashes 2 years earlier. A memorial plaque there gives only his name, dates of birth and death, and the inscription: "Life is a Field of Honour." The former Grenfell home in St. Anthony is now operated as a museum by a non-profit historical society. Grenfell Campus of the Memorial University of Newfoundland is named in his honor. In 1997, Grenfell was inducted into the Canadian Medical Hall of Fame. Wilfred Grenfell was honored philatelically by Newfoundland in 1941 (Scott 252) and by Canada (Scott 438) in 1965 (Figure 1). Figure 2 is a first day cover of the Canadian stamp, mailed from Ottawa on the initial day of postal usage in June 1965. Newfoundland and Labrador had been a separate British colony and later a Dominion during Grenfell's life. Residents voted to join Canada in 1949. The authors report no competing interests.
Late-Phase Clinical Trial
APR 2024ZanwarLeukemia
Treatment patterns for AL amyloidosis after frontline daratumumab, bortezomib, cyclophosphamide, and dexamethasone treatment failures
The immediate goal for therapy in patients with systemic immunoglobulin light chain amyloidosis (AL) is to swiftly achieve at least a hematologic very good partial response (VGPR), given the consistently improved organ responses and survival with achievement of deep hematologic responses [ 1 , 2 , 3 ]. The phase III ANDROMEDA trial demonstrated that the addition of daratumumab to bortezomib, cyclophosphamide, and dexamethasone (D-VCd) resulted in significantly higher hematologic CR (53%) and VGPR rates (78%) compared to VCd in previously untreated patients [ 4 ]. These outstanding response rates have led to D-VCd being the currently accepted frontline therapy for AL amyloidosis. However, up to one-fourth of patients do not achieve a deep response (≥VGPR) with D-VCd induction and may need subsequent treatment to improve the response depth [ 4 ]. Data guiding the selection of subsequent treatment in these patients are limited, and here we report on the patterns of treatment failure and subsequent therapies in this cohort of patients.
Original Research
MAR 2024GoelBlood Cancer Journal
Outcomes of patients with multiple myeloma refractory to standard dose vs low dose lenalidomide
Retrospective study demonstrates equivalent progression free survival in standard- and low-dose lenalidomide-refractory multiple myeloma, indicating drug resistance is dose-independent.
Original Research
JAN 2024AndersoneJHaem
A case of benign immunoglobulin D monoclonal gammopathy of undetermined significance with 26 years of follow‐up
The presence of a serum immunoglobulin D (IgD) monoclonal protein (M-protein) is seen in < 1% of patients with monoclonal gammopathies and is usually indicative of a malignant plasma cell disorder. Only a few cases of well-documented benign monoclonal gammopathy of undetermined significance (MGUS) of IgD subtype have been reported, and only 2 of those had over 5 years of follow-up at the time they were reported. Herein we describe longer-term follow-up of one of those 2 patients who has subsequently passed away from unrelated causes but never developed multiple myeloma or amyloidosis after 26 years of follow-up. Although IgD MGUS is extremely rare, this case confirms that presence of an IgD M-Protein is not always synonymous with a malignant plasma cell process.
Prognostic Study
DEC 2023AbdallahBlood Cancer Journal
Muscle and fat composition in patients with newly diagnosed multiple myeloma
Measures of muscle and adipose tissue mass have been associated with outcomes in several malignancies, but studies in multiple myeloma (MM) are inconsistent. The aim of this study was to evaluate the association between muscle and fat areas and radiodensity, and overall survival (OS) in patients with newly diagnosed MM. We included 341 patients diagnosed with MM from 2010–2019 who had an 18 F-fluorodeoxyglucose positron emission tomography/computed tomography at diagnosis. A cross-sectional image at the third lumbar vertebrae was segmented into muscle and fat components. Median follow up was 5.7 years. There was no association between sarcopenia and baseline disease characteristics or OS. Low muscle radiodensity was associated with higher disease stage, anemia, and renal failure. OS was 5.6 vs. 9.0 years in patients with muscle radiodensity in the lower vs. middle/upper tertiles, respectively ( P = 0.02). High subcutaneous adipose tissue (SAT) radiodensity was associated with higher stage, anemia, thrombocytopenia, hypercalcemia, renal failure, and high LDH. OS was 5.4 years vs. not reached in patients with SAT radiodensity in the upper vs. middle/lower tertiles, respectively ( P = 0.001). In conclusion, sarcopenia was not associated with OS in MM patients. High SAT radiodensity and low muscle radiodensity were associated with advanced disease stage and adverse laboratory characteristics.